Seek urgent medical help for jaundice with confusion, unusual drowsiness, fainting, severe or worsening abdominal pain, repeated vomiting, vomiting blood, black stools, new marked swelling or unusual bleeding. These may be signs of acute liver failure or another serious condition. Dehydration, inability to keep fluids down, or a very unwell infant also needs prompt care. Anyone who is pregnant and may have hepatitis E should obtain urgent assessment because severe illness is more likely in pregnancy.
What does hepatitis mean?
Hepatitis means inflammation of the liver. Viruses A, B, C, D and E are important causes, but hepatitis can also result from alcohol, medicines or supplements, toxins, autoimmune disease, metabolic conditions and reduced blood flow. “Acute” describes a recent, shorter illness; “chronic” describes inflammation that persists. The likely course, testing, treatment and risk to others depend on the cause.
Many people have no symptoms, especially early in hepatitis B or C. When symptoms occur they may include tiredness, fever, reduced appetite, nausea, vomiting, discomfort under the right ribs, dark urine, pale stools, itching, joint pain or jaundice. Symptoms cannot identify the virus or distinguish infection from non-infectious liver disease, so laboratory confirmation matters.
How hepatitis viruses differ
Hepatitis A usually spreads by the faecal–oral route through contaminated food or water or close contact, including oral–anal sexual contact. It does not become chronic. Most people recover with supportive care, although acute liver failure can occur rarely. Vaccination is effective where recommended.
Hepatitis B spreads through infected blood and body fluids, including during birth, sex, unsafe injections, shared injecting equipment or unsterile tattooing and piercing. Chronic infection develops in about 95% of people infected in infancy or early childhood but in fewer than 5% infected as adults. A safe, effective vaccine and a timely birth dose prevent infection.
Hepatitis C is blood-borne. Major risks include unsafe healthcare procedures, unscreened blood and shared injecting equipment. Sexual transmission involving blood exposure and transmission during birth occur less commonly. Around 55–85% of infected people develop chronic infection. There is no effective vaccine, but modern direct-acting antivirals cure more than 95% of treated people.
Hepatitis D can occur only in someone with hepatitis B and can make chronic liver disease progress more rapidly. Hepatitis B vaccination prevents HDV in people not already infected with HBV. Specialist assessment is important; newer HDV treatments are available in some regions, while access and eligibility vary.
Hepatitis E is commonly spread through contaminated water; some strains are acquired from raw or undercooked meat. It is usually acute and self-limited, but it can cause severe liver failure, particularly during pregnancy. Chronic infection is rare and mainly reported in immunosuppressed people. A vaccine is licensed in China and some other countries and has been used for outbreak control, but it is not routinely available everywhere.
Finding the cause and measuring liver health
Assessment covers symptoms, travel and food or water exposure, medicines and supplements, alcohol, pregnancy, medical procedures, sexual and blood exposure, family history and other illnesses. Blood tests such as ALT and AST indicate liver-cell injury but do not by themselves show the cause. Bilirubin, albumin and clotting tests help assess liver function and severity, interpreted with examination and the clinical context.
Cause-specific testing may include viral antigen or antibody tests and nucleic-acid tests. For hepatitis C, a positive antibody test shows previous exposure; an HCV RNA test is needed to confirm current infection. Hepatitis B uses a combination of tests to distinguish current, past and vaccine-related markers and may require HBV DNA monitoring. Ultrasound, elastography and non-invasive blood scores can assess scarring. Liver biopsy is reserved for selected questions rather than being required for everyone.
Autoimmune hepatitis cannot be diagnosed by one test. Clinicians combine blood tests, exclusion of competing causes, imaging and sometimes liver biopsy. Testing should be linked to confidential counselling, vaccination or treatment where appropriate and offered without stigma.
Treatment depends on the type and severity
Uncomplicated acute hepatitis A or E is generally managed with rest as needed, fluids and clinical monitoring. Avoid alcohol and check medicines, painkillers and supplements with a clinician or pharmacist; some products can worsen liver injury, and “detox” remedies do not treat viral hepatitis. Severe acute illness requires hospital care.
Acute hepatitis B usually receives supportive care, while selected severe cases need specialist antiviral treatment. Chronic hepatitis B treatment can suppress the virus, reduce progression to cirrhosis and liver cancer and improve survival, but it does not usually eradicate infection and may be long term. Eligibility and monitoring depend on viral tests, liver health, age, pregnancy and other conditions.
Chronic hepatitis C is treated with a short course of oral direct-acting antivirals selected for the individual. Cure is confirmed with follow-up viral testing. Previous infection or cure does not provide reliable immunity against reinfection. Hepatitis D and chronic hepatitis E require specialist care. Autoimmune hepatitis is usually treated with medicines that reduce immune activity; stopping them without supervision can cause relapse.
Preventing infection and protecting the liver
Follow the vaccination schedule in your country for hepatitis A and B; hepatitis B vaccination should start as soon as possible after birth, ideally within 24 hours. Pregnancy screening and timely maternal and newborn care can greatly reduce HBV transmission. There are no effective routine vaccines for hepatitis C or D, but hepatitis B vaccination also prevents D in someone who is not already infected with B.
Use sterile medical, tattooing, piercing and injecting equipment; never share needles or personal items that may carry blood. Screen donated blood, use condoms or other barrier protection when relevant, and make harm-reduction and testing services accessible. Wash hands, use safe water and sanitation, and cook meat thoroughly to reduce hepatitis A and E risk.
Follow-up and outlook
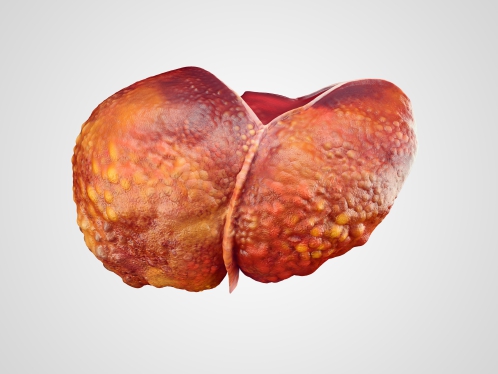
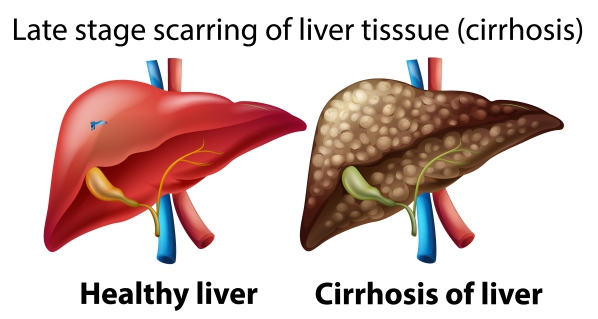
People with chronic hepatitis need an individualized follow-up plan for viral activity, liver scarring, medicine safety and, when indicated, liver-cancer surveillance. Cirrhosis and cancer are possible complications of chronic B, C or D, but progression varies and effective treatment changes risk. Seek advice before alcohol, supplements or new medicines and do not stop prescribed treatment because symptoms improve.
References and further reading
These references were supplied with the article and are provided so readers can examine the supporting material.
- Innes JA, Maxwell SRJ. Davidson’s Essentials of Medicine. 2nd ed. Elsevier; 2016. Legacy reference retained from the original article.
- Kumar P, Clark M. Kumar & Clark’s Clinical Medicine. 9th ed. Elsevier; 2017. Legacy reference retained from the original article.
- Samji N. Viral Hepatitis. 2017. Legacy reference retained from the original article; fuller bibliographic details were not recorded.
- Previsani N, Lavanchy D. World Health Organization. Hepatitis B. 2002. Legacy reference retained from the original article.
- World Health Organization. Guidelines for the prevention, care and treatment of persons with chronic hepatitis B infection. 2015. Legacy reference retained from the original article; superseded by updated WHO guidance.
- World Health Organization. Hepatitis A. Updated 28 July 2026. Accessed 7 September 2026.
- World Health Organization. Hepatitis B. Updated 28 July 2026. Accessed 7 September 2026.
- World Health Organization. Hepatitis C. Updated 28 July 2026. Accessed 7 September 2026.
- World Health Organization. Hepatitis D. Updated 28 July 2026. Accessed 7 September 2026.
- World Health Organization. Hepatitis E. Updated 28 July 2026. Accessed 7 September 2026.
- National Institute of Diabetes and Digestive and Kidney Diseases. Autoimmune Hepatitis. Reviewed March 2023. Accessed 7 September 2026.
- National Institute of Diabetes and Digestive and Kidney Diseases. Diagnosis of Autoimmune Hepatitis. Reviewed March 2023. Accessed 7 September 2026.
- National Institute of Diabetes and Digestive and Kidney Diseases. Treatment for Autoimmune Hepatitis. Reviewed March 2023. Accessed 7 September 2026.