Seek urgent medical assessment after a low-trauma injury if you cannot stand or bear weight, have new severe back pain or a suspected fracture. New leg weakness or numbness, loss of bladder or bowel control, numbness around the groin, or severe pain after a fall needs emergency assessment. Do not delay care to try a home remedy.
What is osteoporosis?
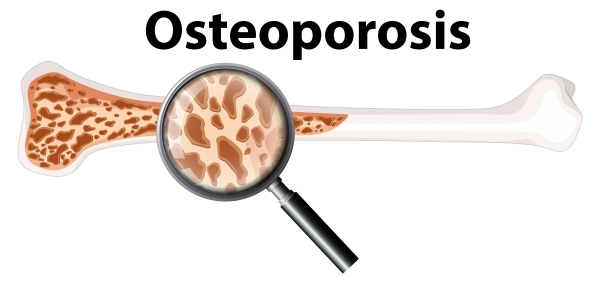
Osteoporosis is a condition in which reduced bone mass and changes in bone structure weaken the skeleton and increase the risk of a fragility fracture. A fragility fracture occurs after low-energy trauma, such as a fall from standing height; some vertebral fractures happen with little recognised trauma. The hip, spine and wrist are common sites, although other bones can be affected.
Bone is living tissue that is continually broken down and rebuilt. With osteoporosis, loss exceeds formation over time. The condition is usually silent until a fracture occurs. Pain, height loss or a curved upper back are often consequences of vertebral fractures rather than early symptoms of bone loss itself.
Who may be at increased risk?
Risk is individual and does not result from one identity or behaviour. Important factors include older age, a previous fragility fracture, a parental hip fracture, menopause or clinically significant hormone deficiency, lower body weight, repeated falls, smoking, higher alcohol exposure and prolonged inactivity. Long-term glucocorticoid treatment and some medicines used for cancer, seizures and other conditions can also affect bone.
Secondary osteoporosis may be associated with coeliac or inflammatory bowel disease, rheumatoid arthritis, endocrine disorders, chronic kidney or liver disease, malabsorption, eating disorders, multiple myeloma and some gastrointestinal or bariatric procedures. Tell the clinician about all medicines and supplements, but do not stop prescribed treatment without advice. Risk tools combine several factors and may guide whether bone-density testing or treatment is appropriate.
Screening and diagnosis
Screening applies to people without known osteoporosis or a previous fragility fracture. The US Preventive Services Task Force recommends screening women aged 65 or older and postmenopausal women younger than 65 who are at increased risk. Evidence is insufficient for universal screening of men, so clinicians use individual judgment. Recommendations differ between countries. Someone with a fragility fracture, a strong secondary cause or symptoms needs diagnostic evaluation rather than waiting for routine screening.
Central dual-energy X-ray absorptiometry (DXA) of the hip and spine is the standard bone-mineral-density test. In postmenopausal women and men aged 50 or older, a T-score of −2.5 or lower at an accepted site supports a diagnosis of osteoporosis, but treatment decisions should not be reduced to one number. Age, prior fractures and other clinical risks matter; a fragility fracture can indicate high risk even when the T-score is above that threshold.
History and examination assess fractures, height change, falls, medicines, nutrition and possible secondary causes. Blood or urine tests are selected from the findings rather than ordered as one mandatory panel. Vertebral imaging may be used for height loss, back pain or other risk indicators. Heel ultrasound can help estimate risk but does not diagnose osteoporosis. CT, MRI, nuclear scans and bone biopsy answer selected questions and are not routine confirmation tests.
Treatment is based on fracture risk
The goal is to prevent fractures while balancing benefits, side effects, other conditions and preferences. People at high or very high risk may need medicine promptly, especially after a recent fracture. Oral or intravenous bisphosphonates are first-line options for many eligible people, but kidney function, upper gastrointestinal problems, dental health, route and planned duration matter. Rare jaw osteonecrosis and atypical thigh-bone fractures should be discussed in context: for people at high risk, the fracture-prevention benefit commonly outweighs these uncommon harms.
Other antiresorptive medicines and specialist anabolic or dual-action treatments may be appropriate for selected patients. After a limited anabolic course, follow-on antiresorptive treatment is generally needed to preserve gains. Menopausal hormone therapy may be considered mainly for selected younger postmenopausal women with low baseline risk of adverse effects. Confirmed hormone deficiency is treated for its cause and does not automatically replace fracture-prevention treatment.
Denosumab must not be delayed or stopped without a clinician-planned alternative because vertebral-fracture risk can rise after missed or discontinued treatment. The FDA warns that it can cause severe hypocalcaemia in advanced chronic kidney disease, particularly in people on dialysis or with CKD mineral and bone disorder. Kidney function, calcium and bone-mineral status therefore need specialist assessment and monitoring in that setting.
Nutrition, movement and preventing falls
A balanced diet should provide adequate calcium, vitamin D, protein and energy. Food sources are generally preferred; supplements are appropriate only when intake, vitamin status and health circumstances justify them. Excess calcium or vitamin D can cause harm or interact with treatment, so avoid assuming that more is better.
Weight-bearing activity, muscle strengthening and balance work can support function and reduce falls, but exercise must suit fracture history, balance and ability. After a fracture, with severe osteoporosis or at high fall risk, ask a physiotherapist or qualified clinician how to move safely and avoid sudden or excessive spinal loading. Practical fall prevention includes reviewing medicines, vision, footwear, gait, lighting, rugs, stairs and bathroom hazards.
Follow-up and outlook
Fractures can cause pain, reduced mobility and loss of independence, but these outcomes are not inevitable. Rehabilitation, pain control and prompt secondary-fracture prevention can improve recovery. Follow-up reviews adherence, side effects, falls, new fractures and whether repeat DXA would change care. Only selected lower-risk people taking a bisphosphonate may be offered a supervised pause after reassessment; there is no self-directed “drug holiday” for denosumab. Report any new fracture promptly so risk and treatment can be reviewed.
References and further reading
These references were supplied with the article and are provided so readers can examine the supporting material.
- J. Alastair, I. and Simon, M. Davidson’s Essentials of Medicine. 2nd ed. Elsevier; 2016. Legacy reference retained from the original article.
- Parveen K, Michael C. Kumar & Clark’s Clinical Medicine. 9th ed. Elsevier; 2017. Legacy reference retained from the original article.
- Elam R. Osteoporosis. 2020. Legacy reference retained from the original article; fuller bibliographic details were not recorded.
- Porter JL, Varacallo M. Osteoporosis. January 2020. Legacy reference retained from the original article; fuller publication details were not recorded.
- Johnston CB, Dagar M. Osteoporosis in Older Adults. Medical Clinics of North America. 2020;104(5):873–884. Legacy reference retained from the original article.
- National Institute of Arthritis and Musculoskeletal and Skin Diseases. Osteoporosis: Diagnosis, Treatment, and Steps to Take. Last reviewed December 2022. Accessed 10 September 2026.
- U.S. Preventive Services Task Force. Osteoporosis to Prevent Fractures: Screening—Clinician Summary. Published 14 January 2025. Accessed 10 September 2026.
- National Osteoporosis Guideline Group. Summary of main recommendations. Updated September 2024. Accessed 10 September 2026.
- National Osteoporosis Guideline Group. Clinical guideline for the prevention and treatment of osteoporosis. Updated December 2024. Accessed 10 September 2026.
- U.S. Food and Drug Administration. FDA adds Boxed Warning for increased risk of severe hypocalcemia in patients with advanced chronic kidney disease taking Prolia (denosumab). Published 19 January 2024. Accessed 10 September 2026.
- Centers for Disease Control and Prevention. STEADI—Older Adult Fall Prevention. Accessed 10 September 2026.
- National Institutes of Health Office of Dietary Supplements. Calcium—Health Professional Fact Sheet. Accessed 10 September 2026.