A stroke is a medical emergency. If a person suddenly develops facial drooping, weakness or numbness—especially on one side—difficulty speaking, loss of vision, loss of balance, or a severe unexplained headache, contact the local emergency service immediately. Do not wait to see whether the symptoms improve and do not drive the affected person to hospital unless emergency transport is unavailable.
What is a stroke?
A cerebrovascular accident, more commonly called a stroke, occurs when blood flow to part of the brain is interrupted by a blockage or by bleeding. Without an adequate supply of oxygen and nutrients, brain cells can be injured or die. Rapid assessment and treatment can reduce death and long-term disability.
Stroke is a major global health problem. The World Health Organization reports that it was the third leading cause of death and disability worldwide in 2021. Stroke can affect adults of any age, although risk generally increases with age and with conditions such as high blood pressure, diabetes and atrial fibrillation.
Types of stroke
Ischaemic stroke
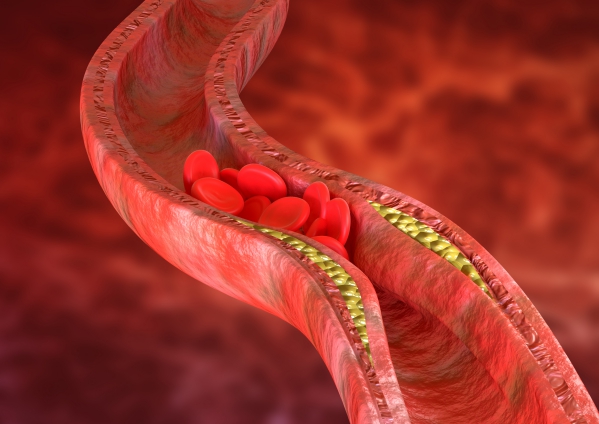
An ischaemic stroke happens when a clot blocks an artery supplying the brain. The clot may form in an artery in the brain or neck, or it may travel from another part of the body—often the heart. Ischaemic stroke is the most common type.
Haemorrhagic stroke
A haemorrhagic stroke happens when a blood vessel ruptures and blood leaks into or around the brain. The bleeding can damage brain tissue and increase pressure inside the skull. Long-standing high blood pressure is an important risk factor, although aneurysms, vascular abnormalities and other conditions can also cause bleeding.
Transient ischaemic attack
A transient ischaemic attack (TIA) produces temporary stroke-like symptoms because blood flow to the brain is briefly interrupted. Symptoms may disappear, but a TIA is still an emergency warning sign and requires urgent medical assessment. It should never be dismissed because the person appears to recover.
Recognising stroke symptoms
Stroke symptoms usually begin suddenly. The B.E. F.A.S.T. reminder covers several common warning signs:
- Balance: sudden dizziness, loss of balance or poor coordination.
- Eyes: sudden loss of vision or a new visual disturbance.
- Face: one side of the face droops or feels numb.
- Arms: sudden weakness or numbness in one or both arms.
- Speech: slurred, unusual or difficult speech, or difficulty understanding speech.
- Time: contact emergency services immediately and note when the person was last known to be well.
Other possible signs include sudden weakness or numbness in a leg, sudden confusion, difficulty walking, vomiting, or a sudden severe headache without a known cause. Symptoms vary according to the part of the brain affected. Only a qualified clinical team can determine whether the event is a stroke and which type it is.
Risk factors
Some stroke risk factors can be modified, while others cannot. High blood pressure is the leading modifiable contributor. Other modifiable factors include tobacco use, high LDL cholesterol, diabetes, physical inactivity, excess body weight, a diet high in sodium, harmful alcohol use and some illicit drugs. Air pollution and kidney dysfunction also contribute to risk.
Factors that cannot be changed include age and a previous stroke. Certain medical conditions—including atrial fibrillation, heart failure and chronic kidney disease—also increase risk and require appropriate clinical management. A family history may contribute, but it does not mean that stroke is inevitable.
How stroke is diagnosed
Emergency clinicians assess the time symptoms began, the person’s medical history, neurological function, blood pressure and blood glucose. Urgent brain imaging—usually computed tomography (CT) or magnetic resonance imaging (MRI)—is essential to distinguish a blocked artery from bleeding, because the treatments are different.
Additional tests may include blood tests, an electrocardiogram to check heart rhythm, imaging of the arteries in the head and neck, and an echocardiogram to look for a possible cardiac source of clots. The choice of tests depends on the person’s condition and should not delay urgent treatment.
Emergency treatment
Treatment depends on the stroke type, the time of onset, imaging findings, medicines already being taken and other individual factors. It must be directed by a specialist stroke team.
Ischaemic stroke
For eligible patients, intravenous clot-dissolving treatment may be given as soon as possible within the appropriate treatment window. Some people with a blockage in a large artery may be eligible for endovascular thrombectomy, in which a specialist removes the clot through a catheter. These treatments are not suitable for everyone and carry risks, including bleeding.
Haemorrhagic stroke
Care may include controlling blood pressure, reversing the effects of anticoagulant medicines when appropriate, managing pressure inside the skull and treating complications in a specialist unit. Some patients need surgery or another procedure to control bleeding or treat an aneurysm. The precise approach depends on where and why the bleeding occurred.
Recovery and rehabilitation
Recovery varies widely and cannot be predicted from stroke type alone. Rehabilitation should begin as soon as the person is medically stable. Depending on the effects of the stroke, the team may include doctors, nurses, physiotherapists, occupational therapists, speech and language therapists, dietitians, psychologists and social-care professionals.
Possible complications include weakness or paralysis, difficulty speaking or swallowing, problems with memory or thinking, pain, seizures, depression, anxiety and loss of independence. Screening and early treatment of these complications are important parts of follow-up care.
Reducing stroke risk
Risk reduction is individualized. Important measures include:
- checking and managing blood pressure;
- not smoking and avoiding second-hand smoke;
- managing diabetes, cholesterol and atrial fibrillation with professional guidance;
- eating a balanced diet with less salt, saturated fat and added sugar;
- being physically active at a level appropriate for the individual;
- limiting alcohol and avoiding illicit drugs; and
- taking prescribed antiplatelet, anticoagulant or lipid-lowering medicines exactly as directed.
Anyone who has experienced a stroke or TIA should follow a personalized prevention plan from their healthcare team. Starting, stopping or changing blood-thinning medicine without medical advice can be dangerous.
References and further reading
These references were supplied with the article and are provided so readers can examine the supporting material.
- World Health Organization. Stroke. Fact sheet published 19 December 2025. Accessed 29 August 2026.
- US Centers for Disease Control and Prevention. Signs and Symptoms of Stroke. Updated 19 May 2026. Accessed 29 August 2026.